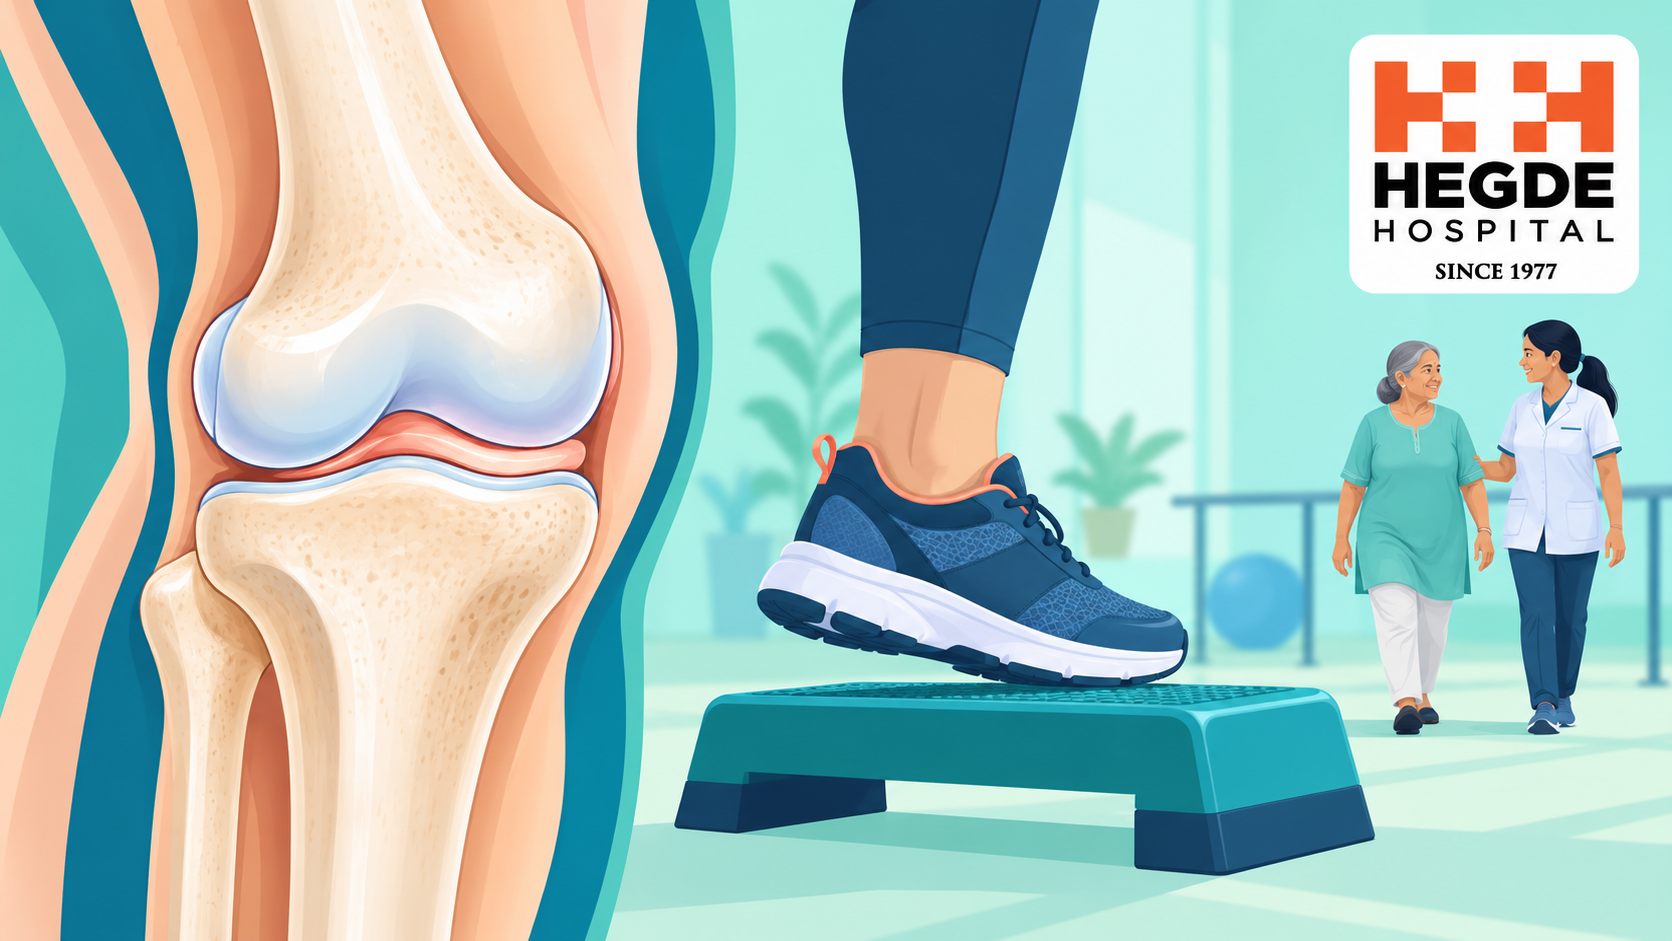
Gradual knee pain can make stairs and walking difficult. Assessment considers symptoms, movement and daily function, rather than an X-ray grade alone.
Climbing stairs, rising from a chair or walking your usual distance has become uncomfortable. An X-ray report may mention reduced joint space, and you wonder whether your knee now needs replacement.
Knee osteoarthritis can cause gradual pain and stiffness, but the report is only one part of the decision. A clinician examines the knee, checks for other explanations and asks what you can and cannot do. Treatment aims to improve comfort and function, with surgery considered when appropriate.
The direct answer
Osteoarthritis is a condition affecting the whole joint, including the cartilage and surrounding structures. It is often described as joint “wear”, but symptoms and progression are more complex than simple rubbing away. Typical knee osteoarthritis can often be diagnosed from history and examination; not everyone needs an MRI or repeated X-rays.
An X-ray grade alone does not decide whether surgery is needed. Pain, stiffness, walking ability, daily activities, previous treatment and your preferences all matter. Many people begin with a supervised non-surgical plan.
Which symptoms fit this pattern?
Pain commonly increases with activity and can make stairs, longer walks or getting up after sitting difficult. Stiffness after rest may ease as you start moving. The knee may feel less flexible, make a grating sound or have intermittent swelling.
These features are not unique to osteoarthritis. Long-lasting morning stiffness, several swollen joints, an injury or symptoms that worsen quickly may suggest another or an additional problem. A click without pain does not establish a diagnosis. Tell the doctor if the knee locks, gives way or is affecting sleep.
What does the doctor examine?
The consultation usually covers when symptoms began, their location, previous injury or surgery, current treatment and other health conditions. Examination may assess walking, alignment, swelling, range of movement, tenderness, stability and muscle strength. Sometimes the hip or back also needs assessment because pain can be referred to the knee.
Bring previous reports and describe a practical limit: for example, how far you walk before stopping or whether you need help with stairs. This is more useful than saying only that the scan is “bad”. You can use the hospital's doctor directory to arrange the appropriate specialist review.
When do X-rays, MRI or blood tests help?
| Assessment | What it can help answer | Important limit |
|---|---|---|
| History and examination | Does the symptom pattern fit osteoarthritis? | Other conditions may need consideration |
| X-ray, when indicated | Are there bone changes or reduced joint space? | The picture does not measure pain directly |
| MRI in selected situations | Is another soft-tissue or joint problem suspected? | It is not routine for typical osteoarthritis |
| Blood tests or joint-fluid testing | Could inflammation, infection or another condition explain symptoms? | No blood test alone confirms osteoarthritis |
Typical symptoms in an adult aged 45 or over, with activity-related pain and no prolonged morning stiffness, may be assessed clinically without imaging. Atypical findings or planning a particular intervention may change the investigation choice. Repeating a scan simply because several months have passed is not always useful.
What can a non-surgical plan include?
Clinician-guided therapeutic exercise is a core part of care. A physiotherapist can tailor strengthening and movement work to your ability, balance and other conditions. The starting level and progression should suit you; a generic exercise challenge is not an individual rehabilitation plan.
Where excess weight adds stress to the joint, supportive weight management can help. A walking aid or selected support may be appropriate after assessment, but every patient does not need a brace. Avoid buying a device only because someone with a different knee problem found it useful.
Pain-relief options may be discussed to support function and rehabilitation. Their suitability depends on your overall health and current treatment. This guide does not select a medicine, injection or regimen. Ask what benefit is realistic, how it will be reviewed and what alternatives exist.
When is knee replacement considered?
A joint-replacement discussion is reasonable when pain, stiffness or loss of function substantially affects quality of life and suitable non-surgical management has not helped enough or is unsuitable. The surgeon reviews your health, examination, imaging and goals with you.
One age, body weight or X-ray grade should not be treated as an automatic yes or no. Individual risks and potential benefits need assessment. Replacement also involves preparation, rehabilitation and follow-up. No procedure can promise a specific recovery date or the same outcome for everyone.
Routine arthroscopic “cleaning” is not recommended simply to treat osteoarthritis. A different diagnosis can require a different discussion; ask exactly what any proposed procedure is intended to address.
How should improvement be reviewed?
Agree a few goals such as walking to the shop, managing stairs or sleeping more comfortably. At review, discuss progress, difficulties with the plan and any new symptoms. The time for follow-up depends on the treatment and your needs; it should not depend only on repeating an image.
Bone health and menopause-related symptoms may also be relevant to some people, but they do not replace a knee assessment. Bring your concerns together so the clinician can consider them without assuming one cause explains everything.
When should I seek earlier assessment?
Arrange routine review for persistent pain or increasing difficulty with activities. A rapidly worsening knee, repeated giving way or persistent swelling needs earlier review. A suddenly hot swollen joint with fever, or inability to bear weight after injury, needs urgent medical assessment rather than waiting for a routine arthritis appointment.
For an individual review of symptoms and previous reports, request an appointment. The hospital services page can help you identify the care pathway.
Frequently asked questions
Does reduced joint space mean I must have surgery?
No. Imaging is considered alongside pain, function, examination and the response to suitable treatment. The report alone does not determine the operation decision.
Do I need an MRI before my first consultation?
Usually not for a typical osteoarthritis pattern. Bring existing reports; the clinician can decide whether further imaging would answer a useful question.
Should I stop all walking because the joint is wearing out?
Not automatically. Suitable activity and therapeutic exercise can help function. Discuss a tailored plan, particularly if pain, instability or other conditions limit movement.
Is a noisy knee always osteoarthritis?
No. Joint sounds can occur without a painful joint disease. Persistent pain, swelling or restricted movement is a reason for clinical assessment.
What if the first treatment plan is not helping?
Return at the agreed review time, or sooner for worsening symptoms. The clinician may reassess the diagnosis, adjust rehabilitation or discuss other options based on your goals.