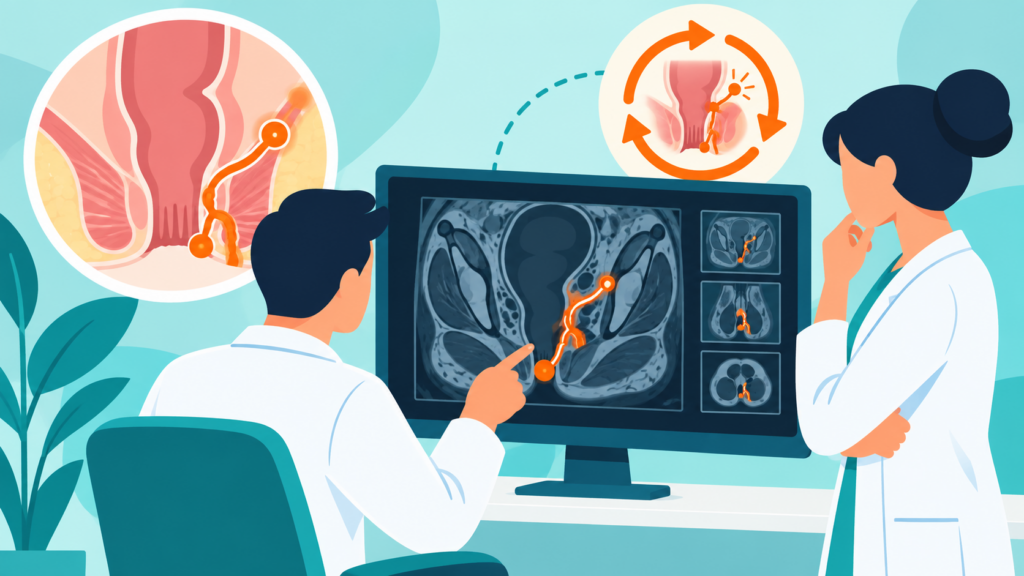
Piles symptoms can recur after any procedure because haemorrhoidal tissue remains part of normal anatomy and bowel-pressure factors may continue. A new examination is needed before repeat treatment.
Yes, piles or piles-like symptoms can return after surgery. Recurrence does not always mean that the first operation was performed incorrectly. Haemorrhoidal cushions are normal structures, different procedures treat different amounts of tissue, and constipation, diarrhoea, pregnancy or repeated straining can create new symptoms over time.
Bleeding or pain after a previous piles procedure should not automatically be labelled recurrence. A fissure, skin tag, scar, thrombosed external pile, infection, inflammatory bowel disease or another colorectal condition may be responsible. Examination helps identify what has actually returned and whether treatment is needed.
What counts as piles recurrence?
Recurrence may mean renewed bright-red bleeding, return of internal prolapse, enlargement of untreated external tissue or symptoms from another haemorrhoidal cushion. Research reports vary because some studies count any minor symptom while others count only prolapse that needs another procedure.
Timing matters. Swelling, tags, discomfort and small amounts of bleeding during expected healing are not necessarily recurrence. Symptoms that appear months or years later have a different context from symptoms that never fully resolved after the operation.
Why piles can return after different procedures
Office procedures and tissue-shrinking techniques intentionally leave more anatomy in place and may have a different recurrence profile from excisional surgery. An operation may treat the dominant cushions but not remove every possible future site. Advanced prolapse, a large external component or incomplete correction of the main problem can also affect the result.
No procedure creates immunity from future haemorrhoidal disease. The meaningful question is whether the method was appropriate for the original grade and anatomy, and whether the current symptom is truly recurrent piles.
Bowel and pressure factors linked with recurrence
Repeated straining, hard stool, prolonged toilet sitting and frequent loose stool can keep stressing the anal cushions. Pregnancy, obesity, chronic cough and activities that repeatedly increase abdominal pressure may also contribute. These factors should be reviewed without blaming the patient, because tissue support and ageing also matter.
A clinician-guided bowel plan can reduce ongoing irritation, but recurrent bleeding still needs assessment. Simply repeating the same cream or old prescription may delay diagnosis of a fissure or another bleeding source.
Would you like clarity about your symptoms?
Share your main symptom, how long it has been present and whether it is getting worse. The Hegde Hospital care team can help you choose the appropriate specialist.
Warning signs that should not be called recurrence
Seek urgent care for heavy or continuous bleeding, black tar-like stool, fainting, severe weakness, rapidly worsening painful swelling, fever or inability to pass urine. Prompt evaluation is also important for anaemia, weight loss, abdominal pain, a persistent change in bowel habit or blood mixed through stool.
Previous piles surgery does not exclude colorectal polyps, inflammation or cancer. Depending on age, family history and screening status, the surgeon may advise colonoscopy or other evaluation even when piles are seen.
How surgeons assess symptoms after previous treatment
Bring the previous operation record if available. The surgeon asks what procedure was performed, whether symptoms ever fully settled, and when bleeding or prolapse returned. Inspection can show tags, fissure, scar, external thrombosis or prolapse. Anoscopy or proctoscopy assesses internal cushions.
The examination also looks for narrowing, poor wound healing, infection and continence concerns. Blood tests may be used when bleeding has been substantial. Colon evaluation is based on the overall bleeding risk rather than the history of piles alone.
Details of the first procedure help distinguish recurrence from residual disease. Useful records include the operation note, discharge summary, pathology report and any later endoscopy. The clinician may ask whether the original symptom was bleeding, prolapse or pain, because recurrence should be compared with the problem that treatment was intended to solve.
A repeat procedure should follow a fresh diagnosis, not simply reuse the previous label. Scar tissue can change the appearance and sensitivity of the area. If there is discharge, a non-healing opening or repeated swelling, the assessment may need to consider an abscess or fistula. If bowel control has changed, this should be discussed openly before planning further surgery.
Can recurrence be prevented completely?
No strategy can guarantee zero recurrence. Risk can be reduced by following the postoperative plan, attending review, addressing constipation or chronic diarrhoea, avoiding prolonged straining and discussing chronic cough or other pressure-related conditions with the appropriate clinician.
Dietary fibre, fluid intake and activity may be included in an individual bowel plan, but abrupt changes are not suitable for everyone, particularly people with bowel narrowing, kidney or heart restrictions, or active digestive disease. Personalised guidance is safer than a universal regimen.
How repeat treatment is chosen
Minor internal recurrence may be suitable for an office procedure, while substantial prolapse, large external disease or failure after several procedures may require surgery. Scar tissue and altered anatomy can make repeat operations more complex, so the original records and an experienced examination are valuable.
The surgeon should explain whether the new plan removes, shrinks or repositions tissue; how it differs from the previous operation; and the expected trade-offs in pain, healing, continence and recurrence. A device-based promise is not a substitute for this analysis.
Do you need a specialist evaluation?
Book a consultation for an examination and an individual plan based on your symptoms, medical history and test results.
Follow-up after repeat treatment
Follow the written plan for bowel regulation, activity, hygiene, wound care and review. Increasing rather than improving pain, fever, heavy bleeding, urinary difficulty, foul discharge or a rapidly enlarging swelling should be reported promptly.
Long-term follow-up is useful when symptoms recur more than once, continence has changed or the diagnosis is uncertain. Keeping a brief record of bleeding, prolapse and bowel pattern can help the clinician judge response without relying on memory alone.
Frequently Asked Questions
How soon can piles recur after surgery?
There is no single timeline. Persistent symptoms soon after recovery may reflect residual disease or another diagnosis, while true recurrence can develop months or years later.
Does recurrence mean I need another operation?
No. The grade, symptom severity, anatomy and previous procedure determine whether observation, an office procedure or surgery is appropriate.
Can a skin tag be mistaken for recurrent piles?
Yes. A tag may remain after swelling settles and does not always require treatment. Examination distinguishes it from active prolapse or thrombosis.
Is laser better for recurrent piles?
Not automatically. Scar, external disease and the pattern of prolapse determine suitability. Ask how the proposed technique addresses the reason for recurrence.
Preparing for a specialist consultation
Before the visit, note when the symptoms began, how often they occur and whether they are linked to meals, bowel movements, lifting, pregnancy or a previous operation. Record the colour and approximate amount of any bleeding or discharge, changes in stool frequency or appearance, fever, weight change and the effect on sleep, work and daily activity. Bring earlier operation notes, discharge summaries, scan or endoscopy reports and recent blood-test results if available.
Share all current prescriptions, allergies, major illnesses, pregnancy status and any history of difficulty controlling stool or urine. Do not stop a prescribed treatment before the appointment unless the treating clinician advises it. A precise history helps the doctor decide whether examination alone is sufficient, whether a test is likely to change management and which treatment trade-offs deserve discussion. If symptoms become severe or an urgent warning sign develops while waiting for the appointment, seek prompt medical assessment instead of waiting for the scheduled visit.
Questions to ask during your consultation
- What was my previous procedure, and is the current problem true recurrence?
- Do I need colon evaluation for the bleeding?
- Why is the proposed repeat treatment different from or better suited than the first?
- How can we address the bowel or pressure factors contributing to symptoms?