Not every painful knee is arthritis, and not every knee needs an MRI first. Symptoms, examination and earlier imaging guide the next step.
Your knee hurts on stairs, after sitting or during a familiar walk. The pain keeps returning, yet you are unsure whether to ask for an X-ray, book an MRI or simply accept that it is age-related. A useful assessment begins with the pattern of symptoms and how they affect movement.
This guide concerns ongoing adult knee pain suitable for a planned consultation. A recent major injury or a hot, rapidly swollen knee needs a different assessment pathway. A scan ordered without a clear clinical question may not explain what is causing your particular pain.
In simple terms
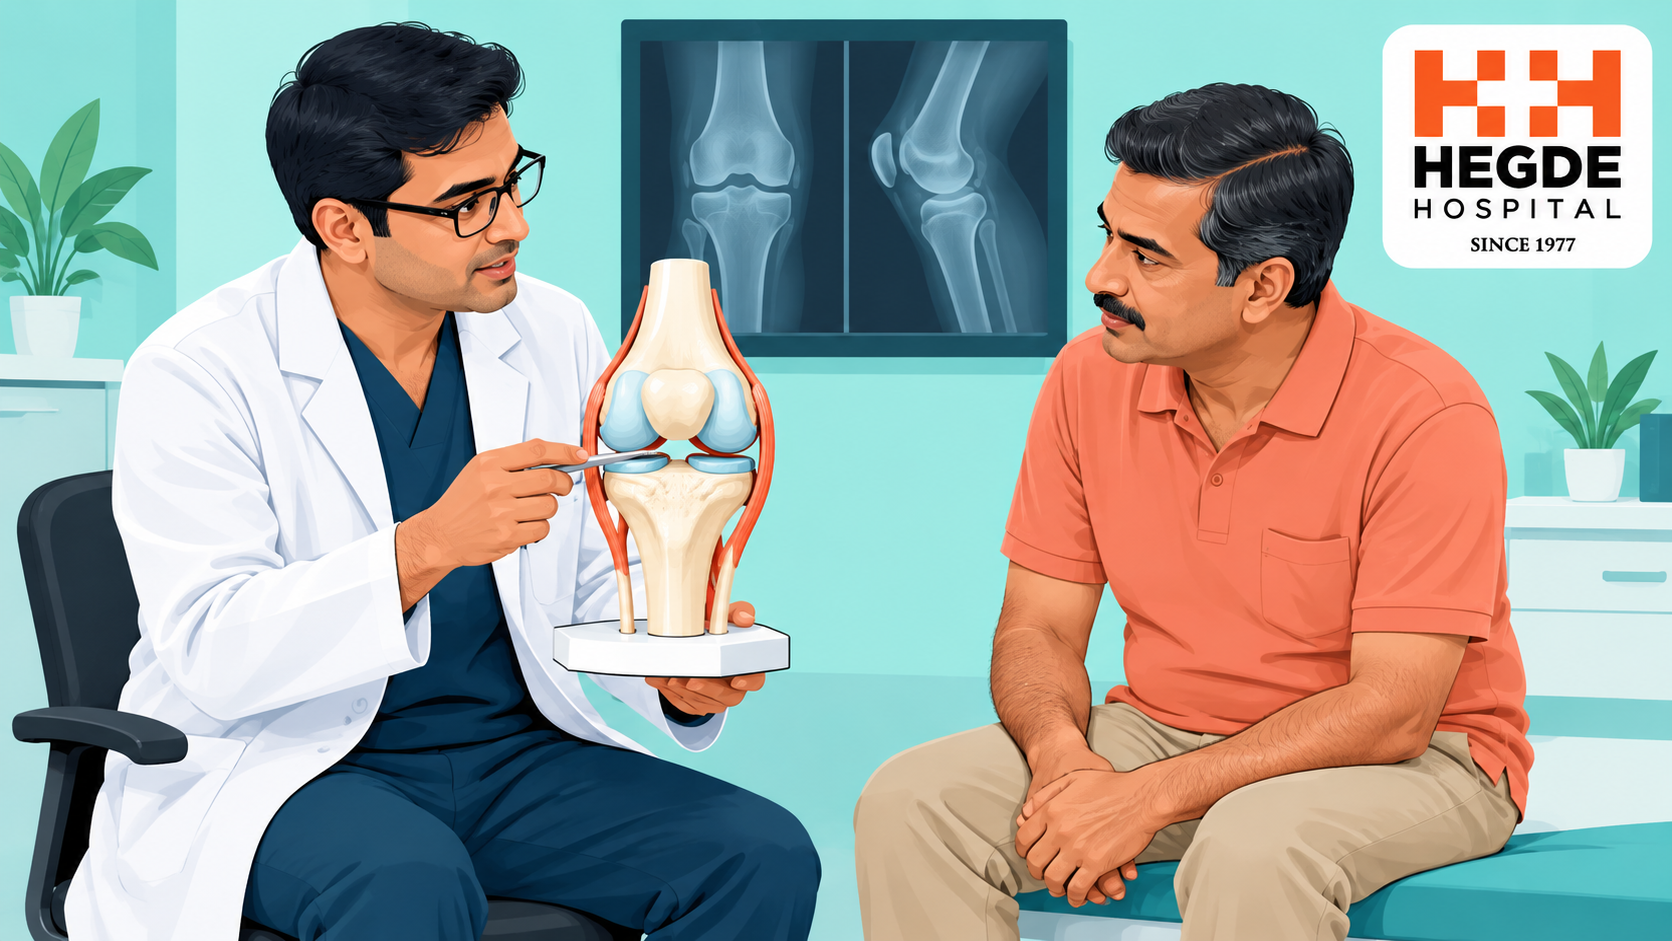
Persistent knee pain can arise from the joint, kneecap region, tendons, meniscus or other structures. Examination helps narrow the possibilities. When imaging is appropriate for chronic knee pain, radiographs are usually the first investigation. MRI is selected when more detail will clarify a suspected problem or change the plan; it is not automatically the first test.
What should you describe at the appointment?
Point to the most troublesome area: front, inner side, outer side or behind the knee. Explain whether the pain follows activity, occurs at rest, or is accompanied by swelling and stiffness. Mention how it affects stairs, standing from a chair, walking distance, sleep and work.
A previous injury, operation or change in activity can be important even if it happened some time ago. Tell the clinician about other painful joints, prolonged stiffness, relevant health conditions and earlier treatment. Bring the actual images where available, not only a written scan report.
The doctor may assess walking, joint movement, tenderness, swelling and stability. Sometimes the hip, back or surrounding muscles also need examination because the perceived site of pain is not always the whole explanation.
Is all persistent knee pain osteoarthritis?
No. Osteoarthritis is common, but pain around the kneecap, tendon-related problems, meniscal abnormalities and inflammatory joint conditions can also cause ongoing symptoms. The likely explanation depends on age, history and examination. A noise from the knee alone does not establish the diagnosis.
Our knee osteoarthritis guide covers that particular condition and treatment decisions. The purpose here is to explain the assessment before assuming every painful knee has the same cause or requires the same operation.
Why might an X-ray come before MRI?
An X-ray, also called a radiograph, shows bone shape, alignment and joint-space changes. It can help identify a pattern of arthritis and other bony explanations. The clinician chooses the views needed for the question, which may include weight-bearing views where appropriate.
MRI gives detailed information about soft tissues and bone marrow, but more detail is not always more useful at the start. Some findings occur without symptoms. Their importance must be judged against the examination and the location of pain.
| Investigation | What it can help clarify |
|---|---|
| X-ray | Bone alignment, joint-space changes and selected bony abnormalities |
| MRI | A suspected meniscus, ligament, tendon or other internal abnormality after clinical assessment |
| Selected blood tests | A specific concern about inflammation or another condition suggested by the history |
This is not a list of tests every person needs. A doctor may decide that the next useful step is rehabilitation or specialist review rather than another scan.
When can MRI help?
MRI may be considered after radiographs when the clinician suspects an abnormality of a meniscus, ligament, tendon or another structure that needs clarification. It may also help when symptoms and initial findings do not fit together and the result would influence management. There is no single pain score that automatically means MRI is required.
Tell the imaging team about implants or metal devices, earlier operations, pregnancy possibility and difficulty with enclosed spaces. The team checks the safety and suitability of the examination. Do not assume every device prevents MRI or that every knee MRI requires an injection.
Once results are available, ask which findings explain the symptoms and which may be incidental. A report that mentions a tear or degeneration is not, by itself, a decision to have surgery.
What if the first plan has not helped?
A follow-up should review the original explanation, whether the plan was practical and whether symptoms have changed. The clinician may assess strength and movement, reconsider another cause, adjust rehabilitation or request an investigation aimed at a specific uncertainty.
Treatment can include an individual activity and rehabilitation plan and other clinician-selected options. Procedures are considered for particular diagnoses and circumstances. This article does not prescribe exercises, home remedies, medicines or a fixed timetable for recovery.
Discuss any concern about weak bones separately. The bone-density assessment guide explains that a bone-density test addresses fracture risk; it is not a substitute for evaluating a painful knee.
When should you seek review sooner?
Arrange a planned assessment when ongoing pain limits daily activities or is not improving over a few weeks. Repeated giving way, persistent swelling or increasing pain deserves prompt clinical review. A knee that becomes locked, cannot bear weight, changes shape, or is hot and swollen with fever needs urgent medical evaluation. Do not wait for a routine scan booking in that situation.
For a stable concern, use the hospital's doctor directory to seek orthopaedic advice and bring your earlier records to the appointment. Ask what the next step is intended to change.
Questions patients often ask
Should I get MRI before seeing an orthopaedic doctor?
Usually an assessment comes first. The clinician can decide whether imaging is needed and which test answers the relevant question. MRI is not routinely the initial investigation for chronic knee pain.
Does a normal X-ray mean there is no knee problem?
No. X-rays show some structures better than others. Persistent symptoms still deserve interpretation alongside examination. Further testing is selected when it would clarify a suspected cause or change care.
Does a meniscus finding on MRI mean surgery is necessary?
No. The finding must fit your symptoms, examination and circumstances. Some changes are incidental. The decision considers the specific problem, function and response to an appropriate treatment plan.
Is a clicking knee always abnormal?
Painless clicking can occur normally. Painful clicking, locking, swelling or giving way should be described to a clinician. The sound alone cannot determine the diagnosis or the need for a scan.
Will a bone-density scan explain my knee pain?
It usually answers a different question: bone density and fracture risk. Knee pain needs its own assessment. Your doctor can explain whether you need either investigation, both or neither.