
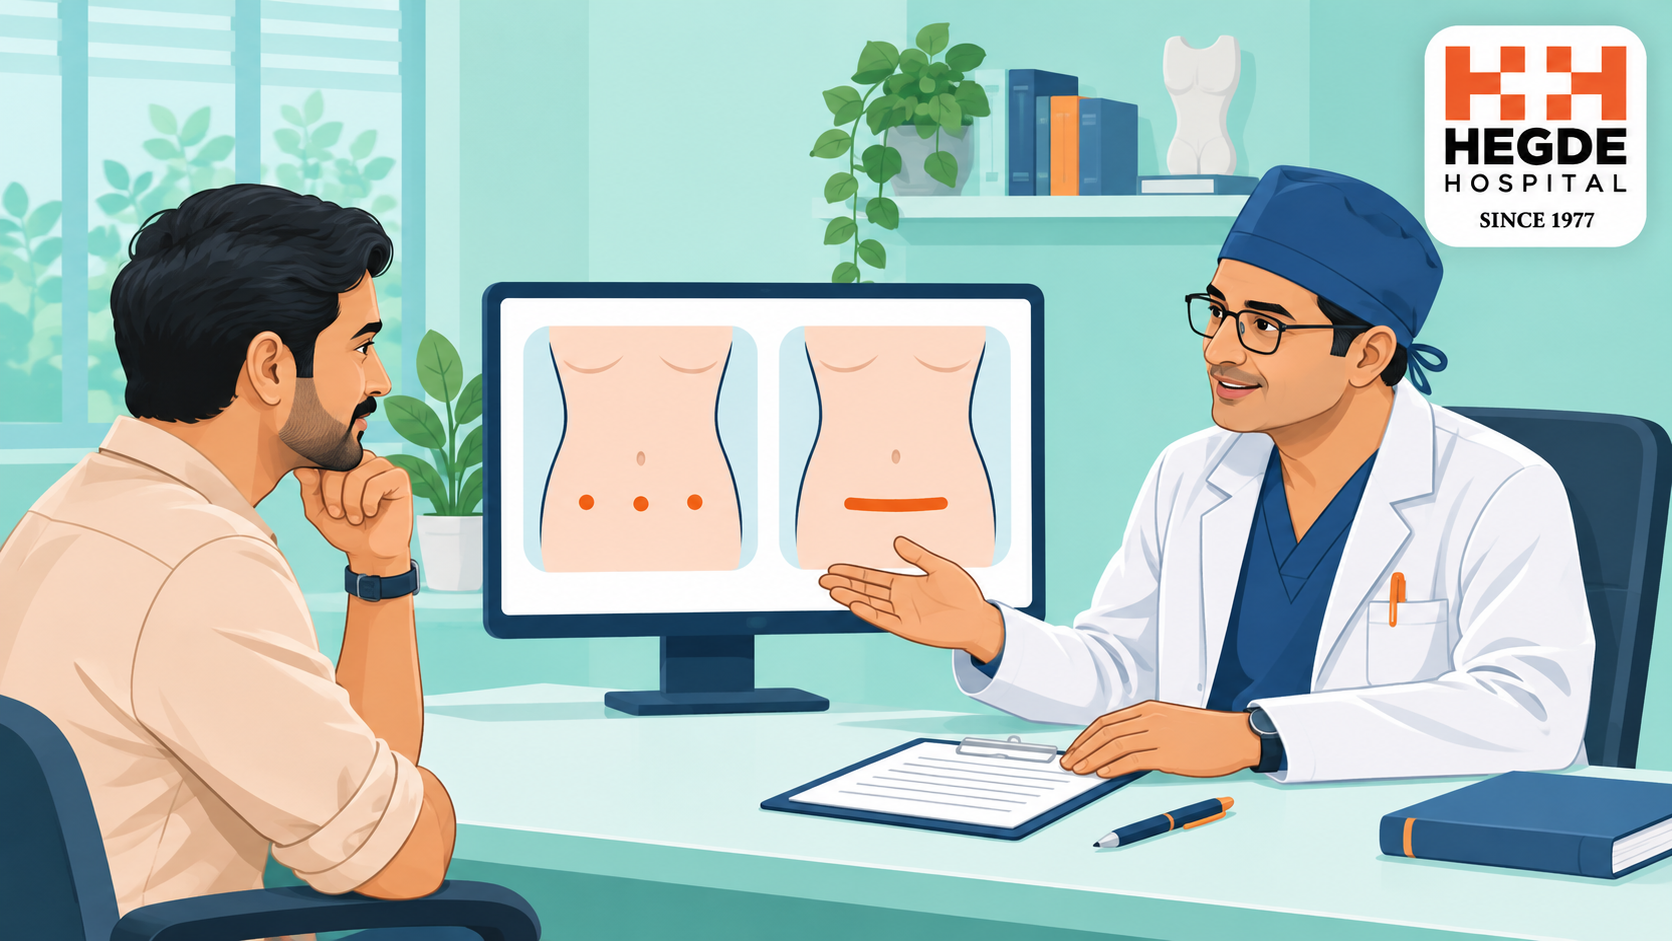
Learn why planned keyhole surgery may need a larger incision, what consent should cover and how the actual operation can change recovery advice.
Before a planned keyhole operation, your surgeon may explain that a larger cut could become necessary. This possibility can feel surprising when you expected small incisions. It belongs in the consent discussion so you understand both the intended approach and the alternatives.
This article explains that planned conversation. The reasons and recovery implications differ between operations; your surgeon should relate them to the procedure proposed for you.
The direct answer
Conversion means changing from laparoscopic access, using a camera and small openings, to an open approach with a larger incision. It may be needed when the surgeon cannot see structures clearly enough or cannot complete the operation safely through the smaller openings. Conversion alone does not establish that the operation failed or that an error occurred.
What can make the smaller approach unsuitable?
Inflammation can make tissue difficult to separate or important structures harder to identify. Adhesions, which are bands of internal scar tissue, can restrict access. Anatomical differences or unexpected findings can also change what is feasible.
Sometimes bleeding, injury or another difficulty requires wider access. These are possible reasons, not events every patient should expect. A change of approach may be a deliberate safety decision; the operative findings and explanation matter more than the incision alone.
Our laparoscopy overview explains the basic approach. This article addresses the narrower question of why the plan may change.
Can the surgeon know beforehand?
Previous operation records, examination and relevant imaging can identify factors that may make surgery more complex. They do not reveal every detail of the tissues or guarantee that conversion will or will not happen.
Tell the surgeon about earlier abdominal operations and any problems during previous procedures. Ask how your particular diagnosis affects access and what alternative approaches might be considered. An individual explanation is more useful than a percentage taken from a study of a different operation or patient group.
Does conversion mean a complication happened?
Not necessarily. A surgeon may change access before an injury occurs because the view or working space is inadequate. Conversion can also be used to deal with a complication. These situations should not be collapsed into a single assumption.
After surgery, ask what was found, why the approach changed and whether anything happened that needs additional follow-up. The discharge summary and operation record can help clarify the answer. A larger wound by itself cannot tell you the full story.
What should consent cover?
Ask about the planned operation, expected benefits, important risks, reasonable alternatives and the possibility of wider access. Find out whether the underlying procedure might also change in particular circumstances and how those possibilities apply to you.
For planned gallbladder surgery, the preoperative assessment guide covers the separate health and preparation review. Follow your own team's instructions about eating, drinking and existing treatment; a general article cannot supply an individual preparation plan.
How might recovery change?
A larger incision can mean more wound discomfort and a longer recovery than originally expected. Hospital stay, walking, lifting, driving and returning to work depend on the actual procedure, findings and your progress. Conversion does not produce one fixed recovery timetable.
Before leaving hospital, ask which instructions replace the original keyhole plan, how the wound will be checked and whom to contact with concerns. If work involves lifting or prolonged travel, describe it rather than asking only when you can return to work.
What should you bring to the follow-up?
Bring the discharge summary, relevant earlier records and your questions. Ask whether any results remain outstanding, what progress is expected and which activities still need clearance. Explain symptoms that are worsening rather than gradually improving.
Follow your discharge advice for prompt review of new fever, wound discharge or increasing pain. Severe new pain, breathing difficulty or faintness needs immediate medical evaluation. Contact the treating team using your discharge instructions.
For a planned discussion, the general surgical and laparoscopy service can help direct your appointment to the appropriate team.
For appointment coordination, contact the team or request a consultation.
Frequently asked questions
Is conversion the same as failure?
No. It describes a change of access. The surgeon's findings and explanation establish why it was needed and what was completed.
Does previous abdominal surgery always require an open operation?
No. Earlier surgery may affect access, but the individual assessment determines the proposed approach.
Can a normal scan rule out conversion?
No. Imaging is useful but cannot predict every finding or difficulty during an operation.
Will I need a second anaesthetic if access changes?
The change is usually made during the same operation. Ask your team what happened in your particular case.
Can I follow the original keyhole recovery timetable?
Confirm the updated plan. Your actual operation, wound and progress determine activity and follow-up advice.