An anal abscess is an infected cavity that often causes acute pain and swelling; an anal fistula is a persistent tunnel that may cause recurring discharge after an abscess.
An anal abscess and an anal fistula are related but not identical. An abscess is a collection of infection near the anus and often causes rapidly worsening pain and swelling. A fistula is a tunnel between the anal canal and skin that commonly remains after an abscess and causes repeated drainage.
An abscess can require urgent drainage, while a fistula usually needs planned mapping and a procedure that protects sphincter muscle. Waiting for an abscess to “burst” can allow infection to worsen, and closing only the outer fistula opening does not treat the internal connection.
What the condition is and why the symptom pattern matters
An abscess is an infected cavity containing pus; a fistula is the tract connecting an internal anal opening to skin. One can exist without an obvious history of the other, and a deep abscess may produce severe pain without a visible surface lump.
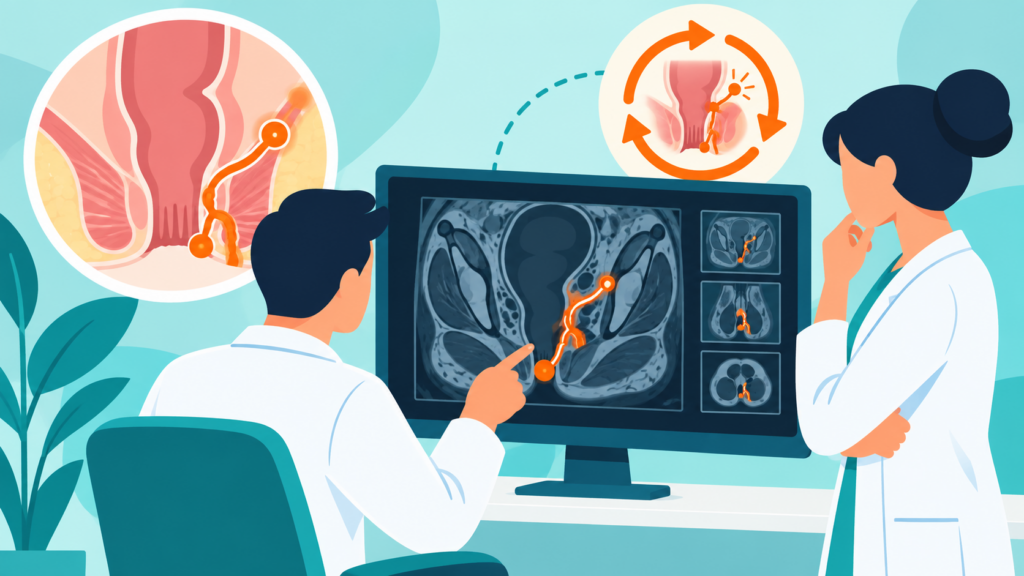
Abscess symptoms are usually acute and progressive. Fistula symptoms often cycle: swelling and pain build, drainage occurs, relief follows, and the outer opening may temporarily seal before the process repeats. Symptoms can overlap with other conditions, so the pattern guides assessment but does not replace an examination. The duration, severity and effect on daily life help determine how quickly evaluation is needed.
Common symptoms and how they may progress
Abscess commonly causes constant throbbing pain, tenderness, warmth, swelling and sometimes fever or difficulty sitting. Fistula more often causes a small recurrent opening, pus- or blood-stained discharge, skin irritation and repeated episodes of swelling. Either can be more complex than it appears externally.
People do not always experience every feature, and symptom intensity does not reliably show how advanced the problem is. Note what triggers symptoms, whether they settle completely, and whether bleeding, discharge, swelling, altered bowel habits or weight change accompanies them. This timeline is often more useful than a single symptom description.
Causes and risk factors
Most cases begin with infection of an anal gland. A fistula can persist after spontaneous or surgical drainage. Recurrent or complex disease may be associated with inflammatory bowel disease, previous surgery, trauma or less common infections and should trigger a broader review.
A risk factor raises probability but does not confirm the diagnosis. Several factors can act together, and sometimes no clear trigger is found. The clinician should also consider previous operations, pregnancy, long-term medical conditions, family history and changes in bowel function when these are relevant to an anal abscess or fistula.
Would you like clarity about your symptoms?
Share your main symptom, how long it has been present and whether it is getting worse. The Hegde Hospital care team can help you choose the appropriate specialist.
Warning signs and when to seek urgent care
Severe increasing pain, fever, chills, rapid swelling, confusion, weakness or difficulty passing urine requires urgent medical assessment. People with diabetes, immune suppression or significant other illness may deteriorate faster and should not delay review because a lump is small.
Urgency depends on the complete clinical picture. Rapid deterioration, fainting, confusion, inability to keep fluids down, uncontrolled bleeding or severe pain with fever should not wait for a routine appointment. Persistent but less dramatic symptoms also deserve timely review when they recur, disturb sleep, restrict eating or activity, or do not improve as expected.
How doctors evaluate the problem
Inspection and gentle palpation may identify swelling, tenderness, scars or an external opening. A deep abscess may need examination under anaesthesia. For fistula, the surgeon assesses drainage sites, prior scars and continence and avoids forceful probing that could create a false tract.
The purpose of evaluation is not merely to attach a label. It is to confirm the likely source, assess severity, identify complications and exclude another condition that would change treatment. Tell the doctor about prior procedures, current prescriptions, allergies and any change in bowel or bladder control, because these details can alter the safest examination and treatment plan.
Tests: which ones may be needed and why
A straightforward superficial abscess may be diagnosed clinically. Ultrasound, CT or MRI may be used for deep, recurrent or complex infection. MRI is especially useful when fistula branches, prior surgery or sphincter involvement must be mapped before definitive treatment.
Not every patient needs every test. A good investigation plan starts with a clinical question: will the result confirm anatomy, identify inflammation or bleeding, rule out a serious alternative, or change the procedure? Unnecessary testing adds cost and delay, while omitting a test that is likely to change management can lead to incomplete treatment.
Treatment options and shared decision-making
An abscess generally needs drainage to control the source; symptom treatment alone does not empty an infected cavity. A fistula plan addresses the tract and internal opening while preserving bowel control. Active infection may be controlled first, with definitive fistula treatment staged later.
Choice of treatment should reflect confirmed diagnosis, severity, anatomy, previous treatment, other health conditions and patient priorities. No responsible plan can promise a painless procedure, zero risk or permanent cure. Ask what the proposed option is intended to achieve, what it cannot correct, what alternatives exist and what would make the team change course.
Do you need a specialist evaluation?
Book a consultation for an examination and an individual plan based on your symptoms, medical history and test results.
When a procedure or surgery is considered
A simple low fistula may suit a tract-opening procedure, while a tract involving more sphincter muscle may need a sphincter-preserving or staged approach. The operation should be based on anatomy rather than the size of the external opening. Complex disease sometimes requires more than one procedure.
Technique names can be confusing and marketing labels may group different operations together. The important details are what tissue is treated, whether muscle or nearby organs are at risk, the type of anaesthesia, expected hospital stay and the balance between recovery and recurrence. Consent should be specific to the proposed operation rather than a generic package description.
Recovery, follow-up and reducing recurrence
Drainage wounds may remain open so infection can clear. Fistula recovery varies with anatomy and procedure. Written instructions should cover dressings, hygiene, bowel movements, activity and review of ongoing drainage.
Recurrence may reflect an undetected branch, persistent internal opening, premature skin closure or underlying inflammatory disease. Contact the treating team for worsening pain, fever, heavy bleeding, repeated vomiting, inability to pass urine, stool or gas, increasing swelling, or a wound that is becoming more inflamed. Planned follow-up matters because symptom relief alone does not always confirm complete healing.
Frequently Asked Questions
Can an abscess become a fistula?
Yes. A persistent tract can remain after an abscess drains, though not every abscess leads to a fistula.
Can a fistula exist without discharge?
Drainage can stop temporarily when the outer opening closes, then pain and swelling may recur.
Is every painful lump an abscess?
No. A thrombosed external pile and other skin conditions can be painful; examination distinguishes them.
Why might treatment be staged?
Controlling infection and protecting sphincter muscle may be safer than attempting every step during acute inflammation.
Preparing for a specialist consultation
Before the visit, note when the symptoms began, how often they occur and whether they are linked to meals, bowel movements, lifting, pregnancy or a previous operation. Record the colour and approximate amount of any bleeding or discharge, changes in stool frequency or appearance, fever, weight change and the effect on sleep, work and daily activity. Bring earlier operation notes, discharge summaries, scan or endoscopy reports and recent blood-test results if available.
Share all current prescriptions, allergies, major illnesses, pregnancy status and any history of difficulty controlling stool or urine. Do not stop a prescribed treatment before the appointment unless the treating clinician advises it. A precise history helps the doctor decide whether examination alone is sufficient, whether a test is likely to change management and which treatment trade-offs deserve discussion. If symptoms become severe or an urgent warning sign develops while waiting for the appointment, seek prompt medical assessment instead of waiting for the scheduled visit.
Questions to ask during your consultation
- Is there an active abscess that needs urgent drainage?
- Does imaging show branches or sphincter involvement?
- Is the fistula simple or complex?
- How will the planned procedure protect continence?