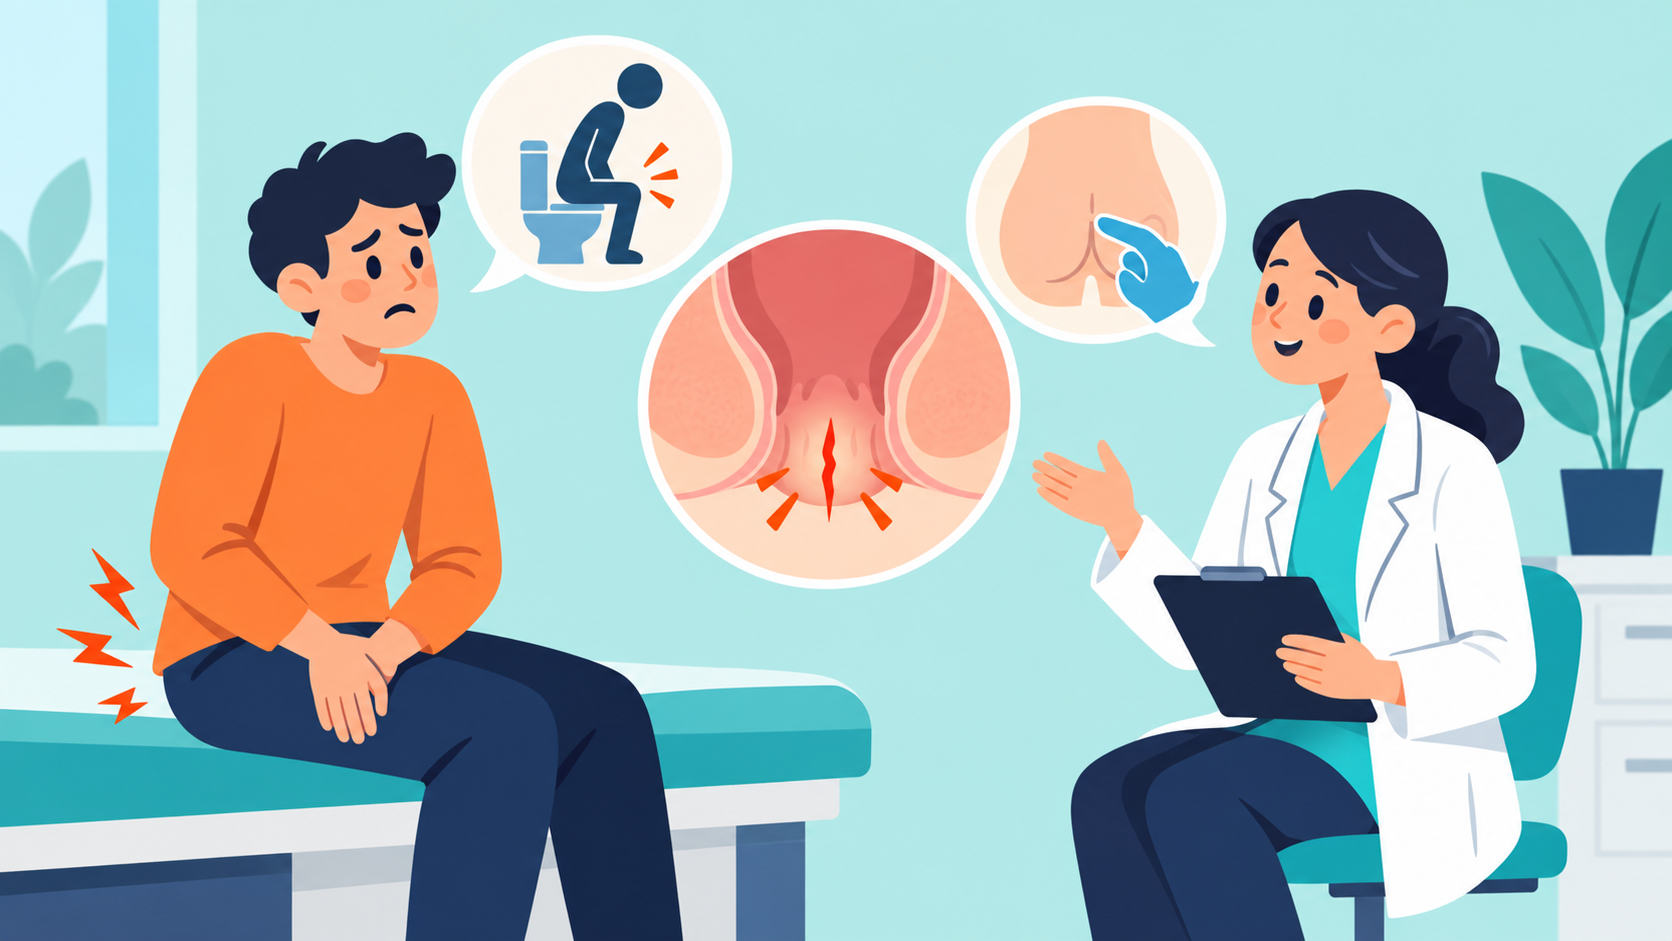
An anal fissure commonly causes sharp pain during stool and burning that continues afterwards, sometimes with a small streak of fresh blood. Other painful anal conditions need to be excluded.
Sharp cutting pain while passing stool followed by burning for minutes or hours is a common pattern of an anal fissure, a small tear in the lining of the anal canal. A streak of bright-red blood may appear on tissue or the stool surface, but bleeding is not always present.
Not every episode of anal pain is a fissure. A painful external clot, abscess, skin inflammation, fistula or another bowel condition can produce overlapping symptoms. Severe or persistent pain should be examined instead of repeatedly treating it on assumption.
What the condition is and why the symptom pattern matters
An anal fissure is a linear tear in the sensitive lower anal lining. Recent fissures may heal when repeated injury and muscle spasm settle; a chronic fissure develops changes such as thickened edges, an exposed internal sphincter or a small external skin tag.
Pain usually peaks during a bowel movement and continues as burning or spasm afterwards. Fear of pain may lead a person to delay stool, allowing it to become harder and continuing the injury cycle. Symptoms can overlap with other conditions, so the pattern guides assessment but does not replace an examination. The duration, severity and effect on daily life help determine how quickly evaluation is needed.
Common symptoms and how they may progress
Typical features are sharp pain with stool, post-stool burning, a small amount of fresh blood and sometimes itching or a small tag. Constant throbbing pain, pus, fever or a rapidly growing swelling points away from an uncomplicated fissure and raises concern for infection.
People do not always experience every feature, and symptom intensity does not reliably show how advanced the problem is. Note what triggers symptoms, whether they settle completely, and whether bleeding, discharge, swelling, altered bowel habits or weight change accompanies them. This timeline is often more useful than a single symptom description.
Causes and risk factors
Passage of hard stool is a common trigger, but repeated loose stool, childbirth, local trauma and inflammatory bowel disease can also contribute. Chronic fissures are maintained by reduced blood flow and persistent sphincter spasm rather than the original injury alone.
A risk factor raises probability but does not confirm the diagnosis. Several factors can act together, and sometimes no clear trigger is found. The clinician should also consider previous operations, pregnancy, long-term medical conditions, family history and changes in bowel function when these are relevant to an anal fissure.
Would you like clarity about your symptoms?
Share your main symptom, how long it has been present and whether it is getting worse. The Hegde Hospital care team can help you choose the appropriate specialist.
Warning signs and when to seek urgent care
Seek prompt care for fever with anal pain, pus, increasing swelling, heavy bleeding, black stool, fainting or severe weakness. Recurrent fissures in an unusual position, weight loss, chronic diarrhoea, abdominal symptoms or poor healing may require evaluation for an underlying disease.
Urgency depends on the complete clinical picture. Rapid deterioration, fainting, confusion, inability to keep fluids down, uncontrolled bleeding or severe pain with fever should not wait for a routine appointment. Persistent but less dramatic symptoms also deserve timely review when they recur, disturb sleep, restrict eating or activity, or do not improve as expected.
How doctors evaluate the problem
Inspection often identifies the tear and its location. A gentle rectal examination or anoscopy may be deferred when acute pain is severe. The clinician assesses whether the fissure is recent or chronic and looks for a clot, abscess, fistula, dermatitis or another bleeding source.
The purpose of evaluation is not merely to attach a label. It is to confirm the likely source, assess severity, identify complications and exclude another condition that would change treatment. Tell the doctor about prior procedures, current prescriptions, allergies and any change in bowel or bladder control, because these details can alter the safest examination and treatment plan.
Tests: which ones may be needed and why
A straightforward fissure often needs no imaging. Blood tests, colonoscopy or evaluation for inflammatory or infectious disease may be considered when symptoms are atypical, recurrent, associated with bowel changes or unexplained bleeding, or when age and screening history justify colon assessment.
Not every patient needs every test. A good investigation plan starts with a clinical question: will the result confirm anatomy, identify inflammation or bleeding, rule out a serious alternative, or change the procedure? Unnecessary testing adds cost and delay, while omitting a test that is likely to change management can lead to incomplete treatment.
Treatment options and shared decision-making
Initial care focuses on making stool comfortable to pass, reducing repeat trauma and allowing the tear to heal under clinician guidance. Persistent symptoms require reassessment rather than indefinite self-treatment. The plan should also address ongoing constipation or diarrhoea that keeps reinjuring the area.
Choice of treatment should reflect confirmed diagnosis, severity, anatomy, previous treatment, other health conditions and patient priorities. No responsible plan can promise a painless procedure, zero risk or permanent cure. Ask what the proposed option is intended to achieve, what it cannot correct, what alternatives exist and what would make the team change course.
Do you need a specialist evaluation?
Book a consultation for an examination and an individual plan based on your symptoms, medical history and test results.
When a procedure or surgery is considered
A procedure is considered for a chronic fissure that has not healed after an adequate supervised plan or causes repeated disabling pain. Options aim to reduce sphincter spasm or treat chronic tissue. Existing continence, childbirth injury and previous anal surgery must be reviewed before any muscle-dividing procedure.
Technique names can be confusing and marketing labels may group different operations together. The important details are what tissue is treated, whether muscle or nearby organs are at risk, the type of anaesthesia, expected hospital stay and the balance between recovery and recurrence. Consent should be specific to the proposed operation rather than a generic package description.
Recovery, follow-up and reducing recurrence
Recovery depends on chronicity and the procedure. Written instructions should cover bowel regulation, hygiene, activity, return to work and review. Pain should trend downward; increasing pain or new swelling needs reassessment.
Recurrence risk is influenced by persistent hard or loose stool, an unrecognised underlying disorder and incomplete follow-up. Contact the treating team for worsening pain, fever, heavy bleeding, repeated vomiting, inability to pass urine, stool or gas, increasing swelling, or a wound that is becoming more inflamed. Planned follow-up matters because symptom relief alone does not always confirm complete healing.
Frequently Asked Questions
Can a fissure bleed without pain?
It can, but the classic pattern includes sharp pain. Painless recurrent bleeding needs evaluation for piles and other colorectal causes.
Is a fissure the same as piles?
No. A fissure is a tear; piles are enlarged vascular cushions. Both can cause fresh bleeding.
Why does pain last after stool?
Irritation of the tear and sphincter spasm can continue after the bowel movement has finished.
When is a fissure called chronic?
Duration, failure to heal and examination changes are considered together; a surgeon confirms the stage.
Preparing for a specialist consultation
Before the visit, note when the symptoms began, how often they occur and whether they are linked to meals, bowel movements, lifting, pregnancy or a previous operation. Record the colour and approximate amount of any bleeding or discharge, changes in stool frequency or appearance, fever, weight change and the effect on sleep, work and daily activity. Bring earlier operation notes, discharge summaries, scan or endoscopy reports and recent blood-test results if available.
Share all current prescriptions, allergies, major illnesses, pregnancy status and any history of difficulty controlling stool or urine. Do not stop a prescribed treatment before the appointment unless the treating clinician advises it. A precise history helps the doctor decide whether examination alone is sufficient, whether a test is likely to change management and which treatment trade-offs deserve discussion. If symptoms become severe or an urgent warning sign develops while waiting for the appointment, seek prompt medical assessment instead of waiting for the scheduled visit.
Questions to ask during your consultation
- Is this definitely a fissure or another painful anal condition?
- Is it acute or chronic, and is the position typical?
- Do I need bowel tests for recurrent or atypical symptoms?
- How will treatment protect bowel control?