Piles, anal fissure and anal fistula can all affect the anal area, but their typical symptoms differ. Examination is important because bleeding, pain or discharge alone cannot confirm the diagnosis.
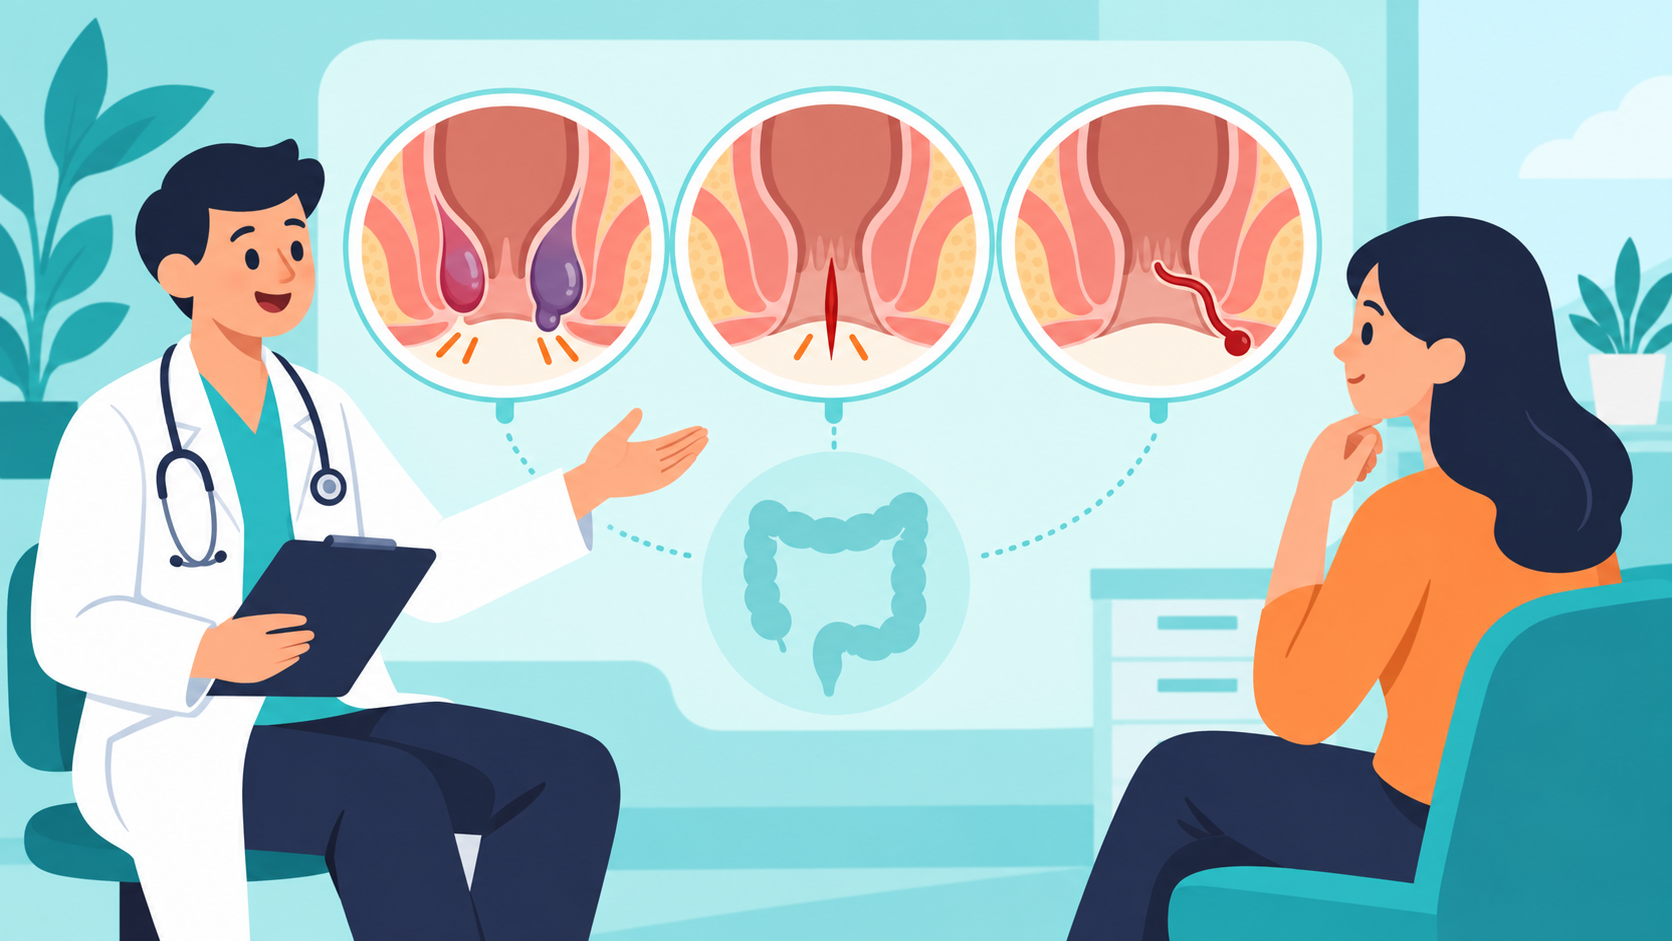
People often use the word “piles” for any pain, bleeding or swelling near the anus. However, piles, an anal fissure and an anal fistula are different conditions. Piles are enlarged vascular cushions, a fissure is a tear in the anal lining, and a fistula is an abnormal tunnel that usually develops after infection near the anus.
The symptom pattern offers clues, but it is not a reliable self-diagnosis. Fresh blood can occur with both piles and fissure; pain may occur with fissure, an abscess or complicated piles; and a fistula may drain only intermittently. A colorectal or general surgeon can identify the source while also checking for less common but important causes of rectal bleeding.
What is the main difference between piles, fissure and fistula?
| Condition | What it is | Typical symptom pattern |
|---|---|---|
| Piles | Swollen haemorrhoidal cushions inside or around the anal canal | Bright-red bleeding, prolapse, itching or a lump; pain is not always present |
| Anal fissure | A small tear in the sensitive lining of the anal canal | Sharp cutting pain during stool, burning afterwards and a small amount of fresh blood |
| Anal fistula | A tunnel between the anal canal and nearby skin | Repeated pus or fluid discharge, a small opening, irritation and episodes of swelling |
These are useful patterns, not fixed rules. A thrombosed external pile can be very painful, a fissure may not bleed every time, and a fistula can temporarily stop draining before symptoms return.
How bleeding, pain, swelling and discharge differ
Bleeding: Piles commonly produce bright-red blood on tissue, on the stool surface or in the toilet. A fissure may produce a smaller bright-red streak associated with sharp pain. Dark-red blood mixed through stool, black stool or recurrent unexplained bleeding needs assessment for a source higher in the digestive tract.
Pain: Severe cutting or burning linked closely to bowel movements suggests fissure. A sudden tender bluish lump can occur with thrombosed external piles. Constant throbbing pain with fever or increasing swelling suggests an abscess rather than an uncomplicated fistula and requires prompt medical attention.
Discharge: Repeated pus-stained or blood-stained drainage from a spot beside the anus is more typical of fistula. Mucus can occur with prolapsing piles, so the colour, smell, location and recurrence pattern matter.
What causes each condition?
Piles are associated with pressure and repeated straining in the anal canal. Constipation, prolonged toilet sitting, pregnancy, obesity and ageing can contribute, but a single factor rarely explains every case. An anal fissure often begins after passage of hard stool, although frequent loose stool, childbirth and local inflammation can also injure the lining.
An anal fistula commonly follows an infection in an anal gland. An abscess may drain spontaneously or be surgically drained, yet a persistent tract can remain. Some complex or recurrent fistulas are associated with inflammatory bowel disease, previous surgery, trauma or other uncommon conditions. This is why recurring discharge should not be treated as a surface skin problem alone.
Would you like clarity about your symptoms?
Share your main symptom, how long it has been present and whether it is getting worse. The Hegde Hospital care team can help you choose the appropriate specialist.
Which symptoms need urgent medical assessment?
Seek urgent care for heavy or continuous bleeding, black tar-like stool, fainting, confusion, severe weakness, rapidly increasing anal swelling, fever with anal pain, inability to pass stool or gas, or severe abdominal pain with vomiting. These features are not typical of a minor uncomplicated condition.
Prompt outpatient assessment is also important for repeated bleeding, unexplained weight loss, anaemia, a persistent change in bowel habit, a family history of colorectal cancer, symptoms beginning later in life, recurrent abscesses or a wound that does not heal. Do not assume that visible piles explain every episode of bleeding.
How doctors distinguish the three conditions
The consultation begins with the timing and character of bleeding, pain, prolapse, swelling and discharge. The doctor may inspect the area and perform a gentle rectal examination when tolerable. Anoscopy or proctoscopy can show internal piles and other anal-canal changes. Severe acute pain may limit examination until it is safer and more comfortable.
Imaging is not needed for every straightforward case. Ultrasound or MRI may be considered when a fistula is recurrent, has several openings, appears to cross important sphincter muscle, or is associated with inflammatory bowel disease. Colonoscopy may be advised when bleeding is unexplained, alarm features are present or age and screening history make examination of the colon appropriate.
Treatment pathways are different
Treatment must match the diagnosis. For piles, the plan may include clinician-guided bowel regulation, an office procedure or surgery depending on grade, bleeding, prolapse and previous treatment. For fissure, the priorities are to prevent repeated injury, reduce sphincter spasm and allow the tear to heal; a persistent chronic fissure may need a procedure after continence risk is reviewed.
A fistula usually requires mapping and a procedure that treats the tract while protecting bowel-control muscles. Simply treating discharge at the skin opening does not remove the internal connection. An active abscess may need drainage first. Complex fistulas sometimes need staged treatment rather than a single operation.
Why one “laser treatment” cannot treat all three in the same way
Laser is a tool used in selected procedures; it is not one universal operation. The anatomy of internal piles, an anal fissure and a fistula is different, so the objective and evidence for each procedure are different. A promotional promise based only on the word “laser” does not explain whether the underlying problem will be removed, whether sphincter muscle is involved or how recurrence will be monitored.
Ask what exact procedure is proposed, why it suits the diagnosis, what alternatives exist, and what the surgeon expects regarding pain, wound care, time away from work, continence and recurrence. The surgeon’s assessment and the correct operation matter more than the marketing label attached to an instrument.
Do you need a specialist evaluation?
Book a consultation for an examination and an individual plan based on your symptoms, medical history and test results.
Recovery and follow-up expectations
Recovery varies considerably. An office procedure for piles, surgery for advanced prolapse, a fissure procedure and a staged complex-fistula operation do not have the same recovery timeline. Discomfort, bowel movements, wound drainage and return to sitting or work depend on the procedure and the individual.
Follow the written discharge plan for food, fluids, bowel regulation, activity, wound hygiene and review appointments. Contact the surgical team for increasing pain, fever, heavy bleeding, inability to urinate, worsening swelling, foul discharge or difficulty controlling stool. Follow-up is particularly important after fistula surgery because external healing does not always confirm that the full tract has resolved.
Frequently Asked Questions
Can piles turn into a fistula?
No. Piles do not transform into a fistula. They can occur in the same person, but a fistula usually follows infection in an anal gland or another inflammatory process.
Is painless bleeding always piles?
No. Internal piles can bleed without pain, but polyps, inflammation and other colorectal conditions may also bleed. Recurrent or unexplained bleeding needs medical evaluation.
Can a fissure cause a lump?
A chronic fissure can have a small skin tag at its outer edge. A lump can also be an external pile or abscess, so appearance alone is not enough.
Does a fistula close permanently without evaluation?
Drainage may stop temporarily if the outer opening seals, but infection and swelling can recur. Persistent or repeated symptoms should be assessed by a surgeon.
Preparing for a specialist consultation
Before the visit, note when the symptoms began, how often they occur and whether they are linked to meals, bowel movements, lifting, pregnancy or a previous operation. Record the colour and approximate amount of any bleeding or discharge, changes in stool frequency or appearance, fever, weight change and the effect on sleep, work and daily activity. Bring earlier operation notes, discharge summaries, scan or endoscopy reports and recent blood-test results if available.
Share all current prescriptions, allergies, major illnesses, pregnancy status and any history of difficulty controlling stool or urine. Do not stop a prescribed treatment before the appointment unless the treating clinician advises it. A precise history helps the doctor decide whether examination alone is sufficient, whether a test is likely to change management and which treatment trade-offs deserve discussion. If symptoms become severe or an urgent warning sign develops while waiting for the appointment, seek prompt medical assessment instead of waiting for the scheduled visit.
Questions to ask during your consultation
- Which diagnosis best explains my symptoms, and were other bleeding causes excluded?
- Do I need anoscopy, colonoscopy or fistula imaging?
- What non-operative and procedural options are appropriate for my exact condition?
- How will the proposed procedure protect continence and reduce recurrence risk?